
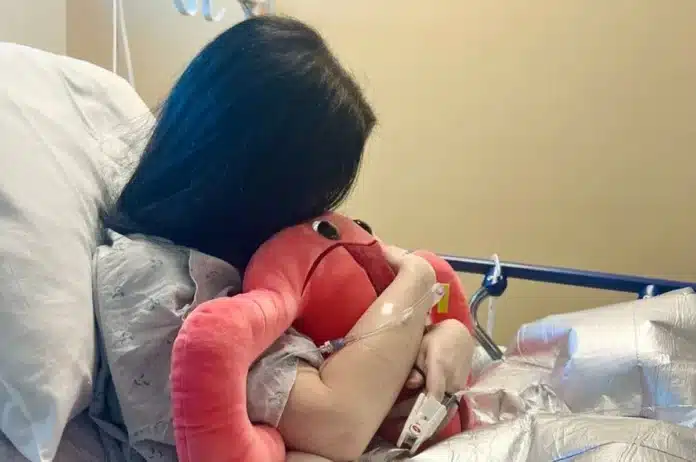
A patient’s prolonged and arduous journey through the healthcare system, marked by persistent pain and unanswered questions, led them to self-educate in radiology to understand their own medical imaging. This experience revealed significant systemic issues, particularly concerning how women’s health concerns are addressed, ultimately culminating in a diagnosis of adenomyosis and the discovery of a pituitary tumor.
The Onset of Unexplained Symptoms
The ordeal began in late 2022 with persistent abdominal pain and a cluster of other unexplained symptoms. An initial scan indicated an issue with the gallbladder, leading to its surgical removal in early 2023. However, the surgery did not alleviate the pain; instead, the patient reported feeling significantly worse. Subsequent consultations with medical professionals, including a nurse practitioner and the surgeon, proved unhelpful. The surgeon initially dismissed the patient’s concerns, suggesting they were seeking drugs, before reluctantly agreeing to another scan. This scan identified a post-operative complication, necessitating a second surgery—a small bowel resection. Following this, an internal bleed required a week-long hospital stay. Despite these interventions, the original pain remained.
Escalating Medical Encounters and a Pattern of Dismissal
By November 2023, the patient was back in the emergency room with severe abdominal pain, leading to a suspected diagnosis of small bowel intussusception. The medical team recommended immediate surgery. Having already undergone two procedures that year, the patient pushed for an MRI beforehand. The MRI showed no intussusception, and the patient was discharged without a clear diagnosis or answers. A visit to a gynecologist resulted in an exploratory surgery that uncovered the uterus had adhered to the abdominal wall, which was surgically corrected. Yet, the pain persisted. When the patient requested to review their own hospital scans, the gynecologist stated, “I’m not a radiologist,” effectively refusing to interpret the images.
This pattern of dismissal continued as the patient approached four different doctors, seeking someone to examine their medical imaging. Faced with a lack of professional willingness to review the scans, the patient resorted to downloading a DICOM viewer—software used for medical images—and began teaching themselves radiology. This self-directed study led to the identification of a potential problem, which was then presented to their primary care provider. For the first time in over a year, this provider listened and agreed with the patient’s findings. A referral to a gynecological oncologist followed, who, after reviewing the scans with the patient, confirmed many of the patient’s self-diagnosed issues. This process, spanning over a year and involving three surgeries, finally led to a diagnosis of adenomyosis, a condition where the uterine lining grows into the uterine wall, often causing severe pain.
Further Discoveries and a Hidden Tumor
In April 2024, the patient underwent a total hysterectomy and unilateral oophorectomy. The surgical findings were extensive: pelvic congestion syndrome, which had never been previously identified; two retained surgical staples from an earlier operation, one of which was sharp and causing irritation; adenomyosis confirmed by pathology; and a severely cyst-ridden ovary. The pathology report served as validation for the patient’s year-long struggle with pain and dismissal.
The medical challenges continued later in 2024 when a new neurologist ordered a brain MRI to investigate long-standing epilepsy. Although the initial call reported a clear scan, months of subsequent symptoms like headaches, dizziness, and fatigue prompted the patient to review the actual radiology report. There, it was noted in plain text: a 1.4-centimeter tumor within the pituitary gland. The neurologist’s office explained that since the tumor was not the focus of their investigation, it was not deemed necessary to report it. This discovery led to further medical consultations, with the primary care provider again being instrumental in referring the patient to an endocrinologist. Despite persistent flagging of low cortisol levels, the endocrinologist was initially dismissive. The patient, having researched secondary adrenal insufficiency, advocated for further investigation, eventually leading to the tumor’s removal in September 2025.
A Near-Fatal Post-Operative Complication
The surgery to remove the pituitary tumor was successful, with cortisol levels normalizing the next day. However, a few days after being discharged, the patient experienced a severe headache, fever, and other alarming symptoms, indicative of a serious infection. An initial ER visit found no emergent issues, and the patient was sent home. A follow-up with the surgeon led to further examination and a blood test order. That night, the patient’s fever spiked to 103.4°F, and they felt critically ill. A message to the surgeon’s physician assistant, accompanied by a photo of the thermometer, prompted an immediate return to the ER. There, the patient was diagnosed with meningitis and sepsis, caused by a rare bacterial strain. Two weeks of hospitalization, multiple lumbar punctures, and eight weeks of self-administered IV antibiotics followed. This critical event underscored the danger of not being believed and the importance of advocating for oneself in the healthcare system.
Systemic Issues and Advocacy for Women’s Health
Throughout these experiences, the patient’s husband provided unwavering support, and their family assisted with childcare. The patient’s employer was also notably supportive during the pituitary tumor ordeal. However, the core battles—understanding medical scans, refusing to be dismissed, conducting research, and navigating the system—were personal responsibilities.
Reflecting on these events, the patient identified a broader pattern affecting women. Statistics reveal that women often wait longer for pain relief in the ER and are less likely to receive adequate pain management compared to men, even with similar reported pain levels. Conditions predominantly affecting women, such as endometriosis and adenomyosis, face significant diagnostic delays, with many patients being told they are exaggerating their symptoms. Adenomyosis, once considered rare, is now estimated to affect up to 1 in 5 women.
The historical exclusion of women from clinical research, with a mandate for considering sex as a biological variable only implemented in 2016 by the NIH, has contributed to a medical system built primarily on male physiology. This foundational gap means that women presenting with complex symptoms may be mislabeled as “difficult” or “anxious” when they are, in fact, actively engaged in self-advocacy due to systemic failures.
Empowerment Through Self-Advocacy
The patient’s journey of becoming their own radiologist, discovering their own tumor, and diagnosing their own condition was not a sign of personal triumph but a stark indicator of systemic shortcomings. The patient emphasizes that their ability to navigate this was due to a combination of stubbornness, a supportive primary care provider, the capacity to understand medical data, and a critical decision to return to the hospital when severely ill. Many women lack these advantages and may not survive similar experiences.
The overarching message is one of empowerment and caution. Patients, especially women, are urged to trust their own bodies, seek multiple opinions, obtain and meticulously review their medical records, and utilize available resources to understand their health. The patient stresses that persistent advocacy is crucial, even when met with skepticism or dismissal. The exhaustion and cost associated with finally being believed highlight the profound challenges women face in receiving adequate healthcare. The experience serves as a powerful reminder that self-knowledge and assertive advocacy are indispensable tools in navigating a healthcare system that too often fails to listen.



